


CCAS – STS Database Update
By David Vener, MD
Chair, Database Committee
The database has been very successful to date. In our first 30 months of operation, we have included data now from 31 sites, with more joining every month. The Fall 2012 harvest, which included data from January 1, 2010 through June 30, 2012 broke down as follows:

The overall adverse event rate was 1.9% (542 events), of which Vascular Access Issues (requiring more than one hour to obtain desired access) was 0.4% (111 events). The next highest event was Unexpected Difficult Intubation at 89 (0.3%). There were 52 episodes of Cardiac Arrest Unrelated to Surgery, which represented 0.2% of all cases. More details on the case mix and adverse events are available online through the CCAS website.
The next version of the dataset has been distributed to the software vendors and goes into effect on July 1, 2013 though I suspect that a number of sites will not implement the updates until January 2014. For anesthesia participants we have made several changes, including streamlining some of the drug options and expanding the adverse event listings based upon feedback from the various sites and CCAS members.
Another development that we will be following with interest is the announcement of a joint STS – Society of Cardiovascular Anesthesiologists (SCA) database for adult cardiac anesthesia. The adult cardiac surgical database has information on over 5 million patients from 1,000 surgeons. The SCA agreement with the STS is somewhat similar to ours, but time will tell how many programs choose to participate in their program.
Unlike our database, the SCA’s dataset is going to be completed on-line through a web-based interface. Finally, multiple members and participants have asked about the interfacing of anesthesia EMR’s directly into their vendor software (for example EPIC Anesthesia or Cerner into CardioAccess).
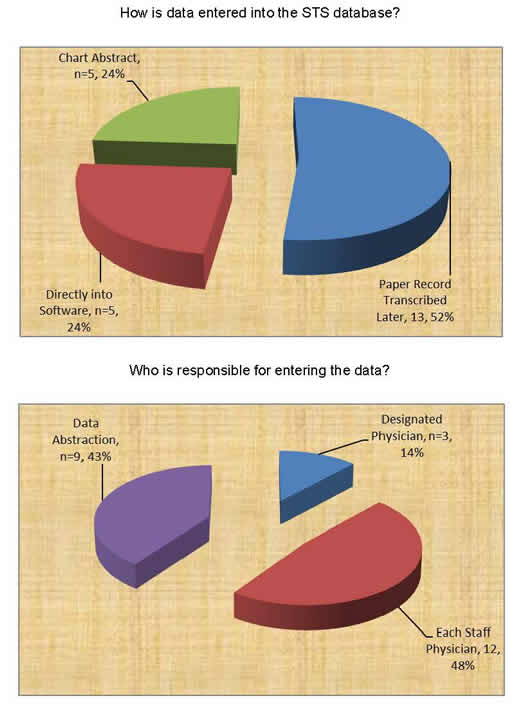
To my knowledge, no group has yet to successfully develop this process – please let me know if you are aware of this being implemented anywhere. For now it appears that approximately 50% of the time a paper record is transcribed into the software after the case is complete, usually by the attending anesthesiologists (see charts below):
Please do not hesitate to contact me if you have any questions about the database or how to participate.
